
Operational growth guide
Discovery-call conversion for cash-pay practices
Discovery-call conversion measures how many attended calls move to the next appropriate paid or clinical step, using a definition the practice applies consistently. Improve it by strengthening pre-call fit, expectation setting, call ownership, scheduling and follow-up rather than pressuring every caller to buy.

Protect the care experience
Operations that support better care conversations.
A useful response, clear preparation and thoughtful follow-up help suitable patients arrive informed and confident. The system supports that experience; it never pretends to provide care.
- Administrative clarity
- Visible human ownership
- Clinical boundaries protected
A calendar can fill with poorly prepared or poorly matched calls while the practice treats every non-conversion as a sales problem. Different team members may also define a converted call differently.
Provider time is consumed, follow-up becomes inconsistent and marketing channels are judged without considering attendance or fit.
For functional, integrative, longevity, concierge and med-spa practices using consultations before a higher-consideration service, the useful unit is not a click, message or isolated booking. It is a visible journey from the original source through a qualified conversation, an appropriate appointment and attendance. That shared definition keeps marketing, operations and the front desk accountable to the same result.
The working model
How should the system be built?
Define qualified, booked, attended and converted states first. Explain the call's purpose before booking, collect only useful business context, prepare the caller and give the team a consistent administrative handoff after the conversation.
- 01
Establish the real baseline
Use a representative period and define each stage in plain language. Separate enquiries, qualified conversations, bookings, cancellations, no-shows and attended appointments so a single blended percentage does not hide the actual constraint.
- 02
Find the point of avoidable friction
Review the patient-facing message, the staff handoff, the calendar rule and the fallback when somebody does not respond. The most expensive gap is often a small operational delay repeated across every enquiry rather than a lack of demand.
- 03
Build one clear next action
Each message should help a prospective patient understand what happens next. Use approved administrative answers, a suitable booking route and a visible way to reach a person instead of a long sequence that creates pressure without clarity.
- 04
Protect clinical and consent boundaries
Automation can acknowledge, route, remind and report. It should not interpret symptoms, decide suitability or continue after a person opts out. Clinical questions and sensitive situations move to the practice's qualified team.
- 05
Measure the downstream result
Judge the change by qualified conversations, bookings and attendance rather than message volume alone. Review staff workload and negative signals as well, because a workflow that converts while overwhelming the front desk is not a durable system.
Implementation detail
What does the setup need?
A reliable implementation is specific enough for staff to operate and simple enough to audit. These are the practical conditions we would validate before launch.
- Separate booking conversion from attended-call conversion.
- Record disqualification reasons without unnecessary clinical detail.
- Review outcomes by source and service.
- Use short follow-up with a clear stop condition.
Set the baseline before changing the workflow and review a sufficiently large period after launch. Segment results by source, service, provider or time window only when the sample supports the comparison. The purpose is a better weekly decision, not a busier dashboard.
YellowHorns reports assumptions beside the result and avoids claiming that one workflow controls revenue, clinical fit or patient choice. That makes improvement slower to exaggerate and easier to trust.
Work, not theatre
What we actually built.
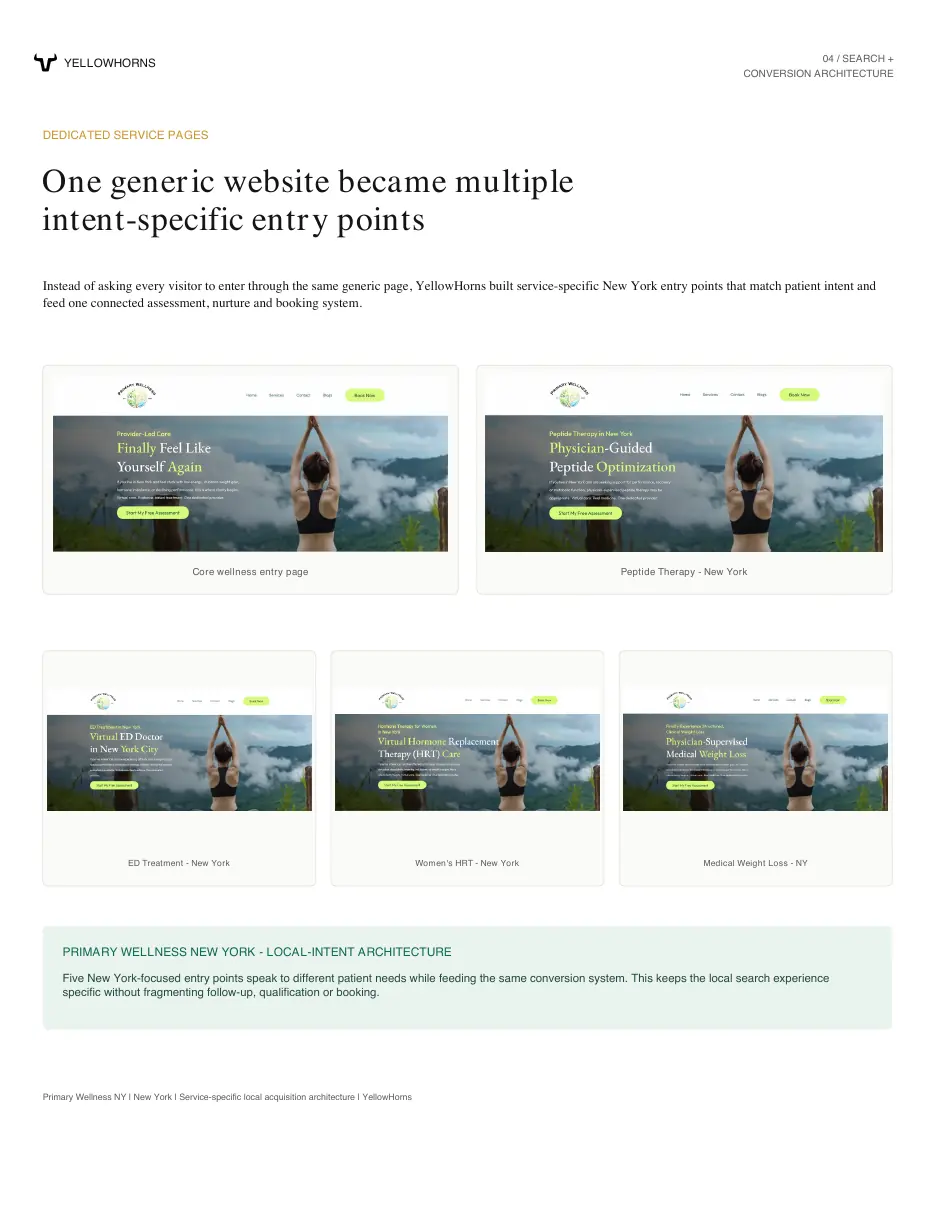
Building a complete patient acquisition system for a telehealth wellness practice
7 to 10 · organic booked consultations per week
Steven Smith, FNP-BCFounder, Primary Wellness NYRead the build notes →How a psychiatry practice turned a confusing digital presence into a clear path to inquiry
Clearer · practice positioning
Erica SmithFounder, AccessMind PsychiatryRead the build notes →
What building the growth engine for a clinical AI platform taught us about practitioner adoption
50+ / month · one-to-one onboarding calls supported with CSR teams
FunctionalMind AIGrowth operations engagementRead the build notes →“We had enquiries coming in, but too many went quiet before the appointment. Now the follow-up feels like a system, not a pile of tools.”
“The big opportunity wasn’t another campaign. It was what happened after someone contacted us. That journey is much clearer now.”
“They found the drop-offs before suggesting more ads. We can finally see and measure the acquisition process.”
“We had demand, but too many ways for people to fall through. The team can now see every opportunity and what needs to happen next.”
“Follow-up used to feel reactive. Now new enquiries, undecided patients and past patients each have an intentional path.”
“We were paying for interest without getting enough consultations. The changes connected enquiries, reminders and reactivation.”
Clear answers
Common questions.
What is discovery call conversion rate?
Discovery-call conversion measures how many attended calls move to the next appropriate paid or clinical step, using a definition the practice applies consistently. Improve it by strengthening pre-call fit, expectation setting, call ownership, scheduling and follow-up rather than pressuring every caller to buy.
What should a practice fix first?
Start with the measurable handoff creating the largest avoidable loss. For functional, integrative, longevity, concierge and med-spa practices using consultations before a higher-consideration service, that means establishing the current journey before adding another campaign, message sequence or software connection.
How long does implementation usually take?
A focused workflow can often be designed and launched in two to four weeks. Timing changes with platform access, approvals, messaging registration, data cleanup, number of locations and the exceptions the practice needs to support.
Does YellowHorns replace the practice team?
No. YellowHorns removes repeatable administrative friction and makes ownership visible. Practice staff keep control of clinical questions, sensitive conversations, approvals and the judgment that a patient relationship requires.
What happens in the free audit?
We review the current discovery call conversion rate journey, identify the first constraint, test the assumptions behind it and explain the narrowest system we would build. The 30-minute session is free and useful even if the practice does not hire YellowHorns.
Free 30-minute growth audit
Bring us the real patient journey.
Answer a few focused questions. We'll review the system, identify the first constraint and prepare one specific recommendation before the call.
Start the interactive audit